Hair Loss and Hormonal Imbalance in Women
Expert advice, tips, and treatments for hair thinning caused by PMOS and hormonal changes.
Understanding Female Hair Loss
Female hair loss often presents as diffuse thinning across the scalp, particularly at the crown and vertex. Unlike male pattern baldness, complete bald patches are uncommon. Hormonal imbalance, especially in conditions like PMOS, is a leading cause.
How PMOS Affects Hair
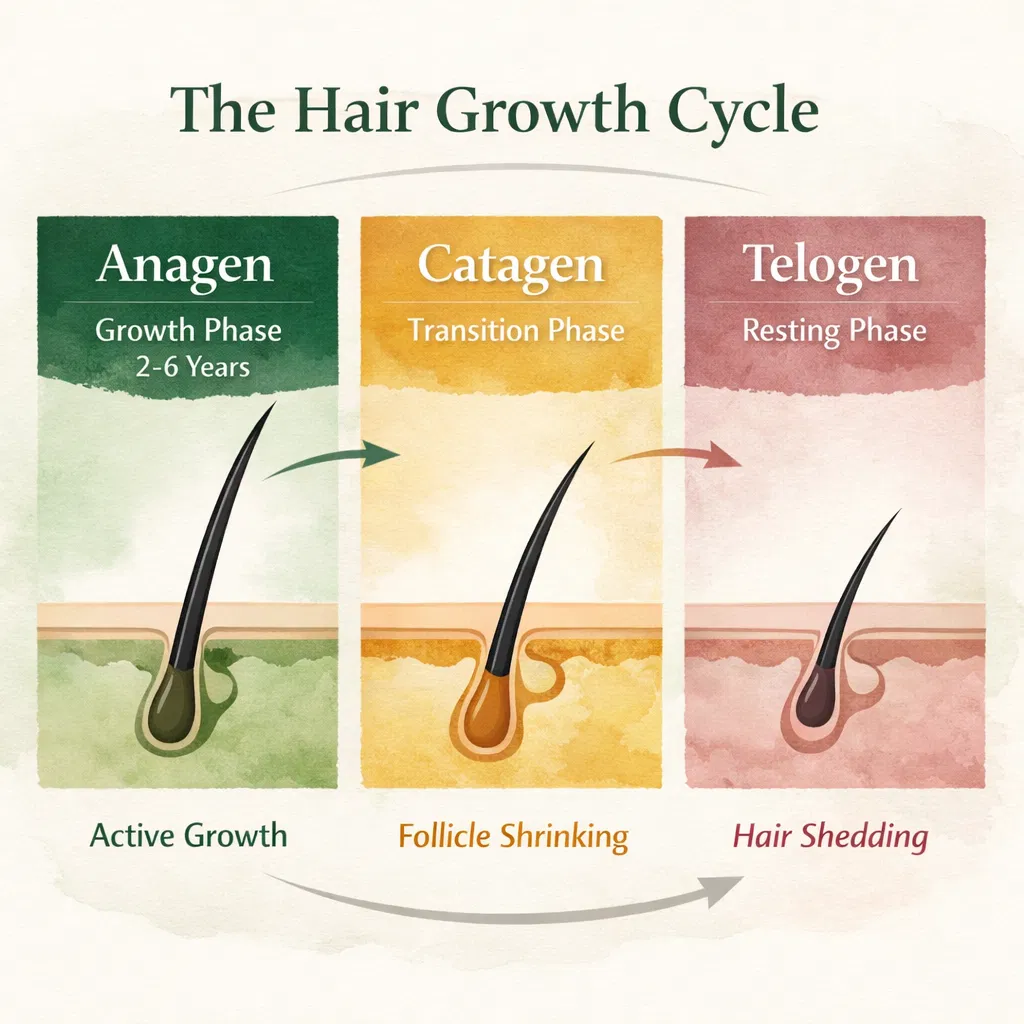
- Hyperandrogenism: High androgen levels shorten the growth (anagen) phase and miniaturize hair follicles, causing thinning.
- Insulin resistance: Common in PMOS, it increases ovarian androgen production and worsens hair loss.
- Inflammation: Low-grade systemic inflammation can weaken hair follicles and exacerbate shedding.
Other Hormonal Imbalances
- Thyroid disorders: Hypothyroidism or hyperthyroidism disrupt hair follicle cycles.
- Prolactin excess: Can inhibit hair follicle activity.
- Estrogen and progesterone drops: Postpartum or perimenopausal changes reduce hair support.
- Other androgen excess: Congenital adrenal hyperplasia or tumors may cause thinning similar to PMOS.
Signs and Symptoms
- Gradual thinning at the crown and vertex
- Increased hair shedding
- Accompanying signs of hyperandrogenism: acne, hirsutism, irregular periods
Diagnosis
A thorough evaluation is essential and typically includes:
- Medical history and medication review
- Physical exam and hair density assessment
- Blood tests: testosterone, DHEAS, LH/FSH ratio, thyroid function, prolactin, fasting glucose/insulin
- Pelvic ultrasound for ovarian morphology
Treatment Options
Management of hair loss associated with hormonal or metabolic factors depends on the underlying cause and the individual’s circumstances.
- Lifestyle: Maintaining a healthy weight, regular physical activity and a balanced diet may support overall metabolic health and, where relevant, improve insulin sensitivity.
- Medical treatments: Depending on the diagnosis, a healthcare professional may consider topical treatments or medicines that influence androgen activity or other pathways involved in hair growth.
- Nutritional support: Where a nutritional deficiency is identified, correcting deficiencies such as iron, vitamin D or zinc may form part of an overall management plan. Biotin supplementation is generally only appropriate when deficiency or inadequate intake is identified.
- Adjunctive therapies: Treatments such as platelet-rich plasma (PRP) or low-level light therapy may be considered in selected individuals. Evidence and suitability vary according to the type and cause of hair loss.
Prognosis
Early detection and targeted therapy can stabilise hair loss and promote regrowth. Genetic predisposition and chronic hormonal imbalance may limit full restoration, but most women experience noticeable improvement with proper management.
References
- Azziz R, Carmina E, Chen Z, et al. Polycystic ovary syndrome. Nat Rev Dis Primers. 2016;2:16057.
- Diamanti-Kandarakis E, Dunaif A. Insulin resistance and the polycystic ovary syndrome revisited: an update on mechanisms and implications. Endocr Rev. 2012;33(6):981–1030.
- Escobar-Morreale HF. Polycystic ovary syndrome: definition, aetiology, diagnosis and treatment. Nat Rev Endocrinol. 2018;14:270–284.
- Hordinsky MK. Female pattern hair loss. Dermatol Clin. 2018;36(1):35–41.
- Ramos PM, Miot HA. Female pattern hair loss: a clinical and pathophysiological review. An Bras Dermatol. 2015;90(1):62–69.
- Rosenfield RL, Ehrmann DA. The pathogenesis of Polyendocrine Metabolic Ovarian Syndrome (PMOS): the hypothesis of PMOS as functional ovarian hyperandrogenism revisited. Endocr Rev. 2016;37(5):467–520.